
What to Do Before Embryo Transfer: What Actually Matters
By the time you reach embryo transfer, the questions tend to get very small — because the stakes feel enormous.
What should I eat? Should I exercise? Should I rest? Should I start something? Stop something? Is there anything I could do now that might matter?
But underneath all of those questions is usually the one that actually matters:
“How do I know what deserves my attention before this transfer?”
Because the answer isn't to do everything.
And it isn't to assume nothing matters either.
It's to understand which questions have a reason to matter in the fertility picture you are actually bringing into this transfer.
You cannot prepare perfectly enough to guarantee implantation
There is no diet, supplement, fertility ritual, mindset or perfectly behaved two-week wait that can guarantee an embryo implants.
Embryo-transfer outcomes involve several factors — including the embryo, the uterus, treatment timing, the transfer procedure, age and chance.
Some of those may be modifiable.
Some are not.
And some may be relevant to one woman but have very little to do with another.
“I can't control everything” is not the same as “there is nothing worth understanding.”
The aim of preparation isn't to give you responsibility for an outcome you cannot completely control.
It's to understand where your attention has a sensible reason to be.
What should you do before embryo transfer?
At the broadest level, embryo-transfer preparation involves a handful of areas:
Your treatment protocol and timing.
Medication, progesterone where relevant, monitoring and transfer instructions belong with your clinic.
Your current health and fertility picture.
Existing diagnoses, deficiencies, symptoms or other medical information may change which wider questions deserve attention.
Your food and nutritional intake.
Not because there is a magical implantation diet, but because “eat well” means very different things depending on what you're already eating and whether there is a genuine nutritional issue.
Your medicines and supplements.
What matters is not how many fertility supplements you can add, but why you're taking them and whether they are appropriate alongside your treatment.
Your movement, recovery and daily routine.
The sensible answer may differ depending on whether this is a fresh transfer after stimulation, a frozen transfer, how you're feeling and what your clinic has advised.
Your previous fertility treatment.
If you've transferred before, what happened is information — even when it doesn't give us a definitive explanation.
Those are the broad areas.
But knowing that still leaves the most important question unanswered:
Which of them actually matters to you?
And that is where generic embryo-transfer advice starts to run out of road.
A checklist can tell you what might matter. It can't tell you what deserves priority in your body
Imagine two women preparing for embryo transfer.
Both have searched exactly the same thing:
“What should I do before embryo transfer to increase success?”
But one is having her first frozen transfer, has no significant symptoms, eats well and has no known deficiency.
The other has previously transferred embryos, has a diagnosed condition, has a documented deficiency and is taking a collection of supplements she has accumulated from different sources.
Giving both women the same ten-point transfer checklist isn't personalised preparation.
It's simply more information.
The important bit is relevance.
What do you already know?
What happened earlier in your IVF treatment?
What has actually been diagnosed?
What are you assuming?
What might deserve a conversation with your clinic?
What are you spending energy on that probably doesn't deserve it?
That is the difference between collecting fertility advice and actually understanding how to use it.
If you’re trying to make sense of what happened between egg collection and the embryos available for transfer, read: What Happens After Egg Retrieval — Eggs, Maturity, Fertilisation & Embryo Development →
Your embryo is being transferred into a body with a history
An embryo transfer doesn't arrive on a blank page.
You arrive with:
your fertility history,
your treatment history,
known diagnoses,
test results,
previous responses to IVF,
nutrition and deficiencies,
medicines and supplements,
symptoms,
sleep and recovery,
and whatever else your body has been dealing with alongside fertility treatment.
That does not mean every symptom is affecting implantation.
It doesn't mean we can take a list of complaints and invent a hidden “root cause”.
But it does mean fertility doesn't happen separately from the rest of your body.
The question is not:
“Which fertility things can I add before transfer?”
It is:
“What does the information I already have give me a reason to pay attention to?”
That's a much more useful starting point.
Your clinic manages the transfer. That doesn't answer every question you have around it.
Your clinic is responsible for the medical treatment.
Medication.
Monitoring.
Progesterone where relevant.
Transfer timing.
The procedure itself.
Their instructions take priority.
But women rarely leave the clinic with only medical-protocol questions.
They go home wondering:
Am I eating properly for this?
Should I still be taking all these supplements?
Does my diagnosis change anything?
What does what happened last time actually tell us?
Can I exercise?
Is this symptom relevant?
Have I missed something?
Those questions aren't necessarily asking your clinic to do something differently.
They're asking:
“How do I make sense of everything around the treatment?”
Can you see how that's a different job?
What should you eat before embryo transfer?
There is no particular “implantation food” proven to make an embryo implant.
So the useful question isn't:
“Which food should every woman eat before transfer?”
It is:
“Is there anything about the way I am currently nourishing myself that genuinely deserves attention?”
For one woman, the answer may simply be that she already eats adequately and there is no reason to overhaul anything.
For another, there may be a known deficiency, highly restrictive eating, poor intake during treatment or another nutritional issue worth addressing.
That's why generic advice such as “eat more Brazil nuts” or “drink pomegranate juice” isn't the same as understanding your nutritional picture.
The food isn't the mechanism.
Knowing whether nutrition is actually a priority for you is the mechanism.
Do you need supplements before embryo transfer?
This is another area where more can easily masquerade as better.
Women often arrive at IVF with supplements recommended by a clinic, fertility coach, friend, podcast, Instagram account or something they found during a late-night search.
The useful questions are not simply:
“Is this supplement good for implantation?”
They are:
Why am I taking it?
What is it supposed to address?
Do I have a reason for that to be relevant?
Does my clinic know I'm taking it?
Am I duplicating ingredients or adding things simply because I'm frightened not to?
A webpage cannot responsibly tell every woman which supplements she personally needs.
But by understanding the reason why you're taking something to support a specific thing your body needs, rather than treating the supplement cupboard as insurance.
Can you exercise before embryo transfer?
There is no single useful answer without knowing where you are in treatment.
Someone having a frozen embryo transfer in a separate cycle is in a different situation from someone only days out from ovarian stimulation and egg retrieval.
Current fertility guidance does not support the idea that ordinary movement after embryo transfer makes an embryo “fall out”, and routine bed rest has not been shown to improve outcomes.
Newcastle Hospitals NHS Foundation Trust
But this is more useful before transfer:
“What is sensible for my treatment stage, my body and the instructions I've been given?”
That is why context matters more than another blanket rule.
IVF Prep helps you work out what deserves your attention — without trying to do everything
IVF Prep by Fertility Bandwidth™ is self-guided video training for the questions that appear before and through IVF.
You don't have to consume it all.
You don't have to turn it into another project.
When a question comes up, go to the relevant training.
Understand what you're actually trying to work out.
See what would make it more or less relevant to your situation.
Know what belongs back with your clinic.
Then move on.
The aim isn't more fertility knowledge.
It's to make the information you already encounter much easier to use.
This is the part Google cannot do for you
Google can give you lists.
It can tell you foods commonly discussed before embryo transfer.
It can tell you about exercise.
Supplements.
Stress.
Transfer-day instructions.
Implantation add-ons.
And by the end you can have twenty tabs open and still be left thinking:
“Yes — but which of this is actually relevant to me?”
That is the problem IVF Prep is designed to solve.
Not by pretending a self-guided programme can diagnose you.
And not by handing you another checklist.
Instead, the training takes the questions that come up before and through IVF and helps you understand:
what the issue actually is,
why it might matter,
what would make it more or less relevant,
when it belongs with your clinic or another professional,
and when you can stop giving it so much attention.
That is a completely different job from giving you more tips.
If you've transferred before, your previous IVF may change the questions worth asking
An unsuccessful embryo transfer is emotionally one enormous event.
But it doesn't automatically tell us the cause.
You may know things about:
the embryo,
the type of transfer,
the uterine cavity,
lining or treatment preparation,
existing diagnoses,
whether implantation has happened previously,
or where other IVF attempts changed earlier in the process.
None of those individually proves an explanation.
But together they can change what deserves attention next.
“It didn't work” is an outcome. It isn't the full analysis.
That's why simply repeating the same generic preparation list before another transfer may not give you what you're actually looking for.
You need to understand what your own history does — and doesn't — justify questioning.
What about pineapple, Brazil nuts, warm socks and bed rest?
These questions deserve answering because they dominate embryo-transfer searches.
But they also show exactly why women become overwhelmed.
There is no specific food proven to make an embryo implant.
Bed rest after embryo transfer has not been shown to improve outcomes; NHS fertility information advises that people can go home afterwards and live as normally as possible without strenuous activity. Newcastle Hospitals NHS Foundation Trust
So the lesson isn't:
“Nothing matters.”
It is:
“Not every thing that gets repeated online deserves equal weight.”
That's the skill I want you to build.
Because today it may be pineapple.
Tomorrow it will be a supplement.
Then an IVF add-on.
Then a symptom.
Without a way of judging relevance, the list never ends.
What if you're considering another implantation test or IVF add-on?
This is exactly where understanding why something is being suggested becomes important.
Some embryo-transfer add-ons are marketed around implantation despite uncertain or unfavourable evidence for improving the chance of having a baby.
For example, the HFEA currently rates endometrial receptivity testing red for most fertility patients and endometrial scratching amber because the evidence is conflicting. Medical Navigator
You don't need to become a reproductive-medicine researcher.
But you should be able to ask:
What problem are we trying to solve?
What evidence suggests I have that problem?
What evidence supports this intervention?
What happens if we don't do it?
An add-on should have a reason to be there. Fear isn't enough.
And learning to ask those questions is part of learning what deserves attention.
REAL FERTILITY EXPERIENCES
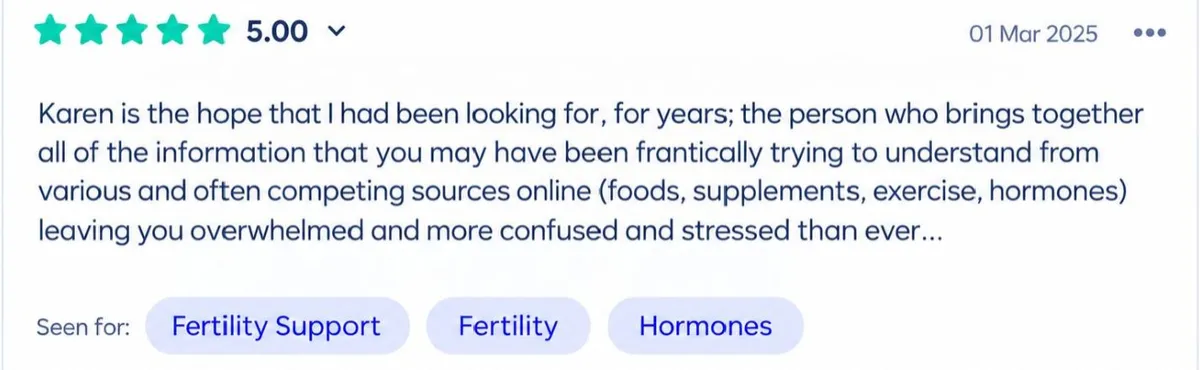
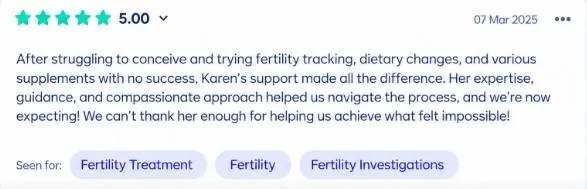
Women came to Karen because they were tired of trying to piece everything together themselves
This is the same problem women repeatedly describe in Karen's wider fertility work:
not a lack of information,
but too much disconnected information and no clear way to decide what actually matters.
Grounded in expertise and personal care, Fertility Bandwidth helps you make sense of fertility decisions with greater clarity and confidence.
© Karen Botha / Fertility Bandwidth™ · Privacy Policy · Terms · Disclaimer